
"*" indicates required fields
"*" indicates required fields
OUTLINE
Copyright © 2000-2014 by Dr. John M . Gettman and Dr. Julie Schwartz Gettman.
Distributed under license by The Gettman Institute, Inc.
OUTLINE
Copyright © 2000-2014 by Dr. John M . Gettman and Dr. Julie Schwartz Gettman.
Distributed under license by The Gottman Institute, Inc.
OUTLINE
Copyright © 2000-2014 by Dr. John M . Gettman and Dr. Julie Schwartz Gettman.
Distributed under license by The Gettman Institute, Inc.
5:30–5:45 pm Film: Addressing Flooding
5:45–7:00 pm Building Friendship and Shared Meaning
7:00–7:15 pm BREAK
7:15–7:40 pm Process of Therapy
7:40–7:50 pm Summary
7:50–8:00 pm What’s Next: Additional Training
8:00–8:45 pm Question and Answer Session
Copyright © 2000–2016 by Dr. John M. Gottman and Dr. Julie Schwartz Gottman. Distributed under license by The Gottman Institute, Inc.
5:30 – 6:15 pm Introduction to Intervention—The Philosophy of the Therapy
6:15-6:40 pm Conflict Management
6:40-7:00 pm BREAK
7:00-8:45 pm Conflict Management, continued
Copyright © 2000–2016 by Dr. John M. Gottman and Dr. Julie Schwartz Gottman. Distributed under license by The Gottman Institute, Inc.
5:30-7:15 pm The Assessment Sessions:
7:15-7:30 pm BREAK
7:35-8:15 pm Film: Assessment
8:15-8:45 pm Question & Answer
Copyright © 2000–2016 by Dr. John M. Gottman and Dr. Julie Schwartz Gottman. Distributed under license by The Gottman Institute, Inc.
5:30 – 7:00 pm The Research: What Makes Relationships Succeed or Fail?
7:00-7:15 pm BREAK
7:15-8:30 pm How to assess a relationship:
8:30-8:45 pm The Assessment Sessions Overview
Copyright © 2000–2016 by Dr. John M. Gottman and Dr. Julie Schwartz Gottman. Distributed under license by The Gottman Institute, Inc.
Use the Build Rituals of Connection” card deck. Split it in half, and each of you look through your half of the cards. From them, choose several rituals of connection that you would like you and your partner to work on. Share your choices with one another, then of those rituals you selected, pick one to work on now. Use the following questions to discuss the details of how you would like to do this ritual together, including getting very specific about the details of your ritual.
The goal for the following exercise is to help you and your partner learn to talk about recovery and to clarify and understand each other’s positions, thoughts, and feelings.
Use the Speaker Listener Guidelines found on the Menu page to help with sharing and listening.
Sit facing each other, with the Listener holding the Your Recovery – Your Wellness card deck. Thumb through the deck until you find several cards that contain something you want to ask your partner to deepen your understanding of your partner’s recovery- wellness experience. You can modify ideas from the card deck or ask something relevant to you that may not be in the deck. Be respectful of your partner’s option to pass on the question or to limit or modify the question. Think of this as an interview not a two-way conversation. The focus is on understanding your partner’s perspective NOT sharing yours. Avoid questions or answers that may lead to anything that relates to the relationship or relationship recovery.
Remember these are the Speaker’s experiences, feelings, and needs. Respond simply with an accepting presence and an indication that you hear and understand. You do not have to fix, change, or take responsibility for what you hear.
Only answer questions you are comfortable and willing to talk about. You may pass on or modify any question, or stating, “I’ll pass on that one,” or “That is all I want to say about this for now.” Help your partner understand what you think is important for your partner to know about your thoughts and feelings about recovery-wellness.
After 15 minutes (or an agreed upon amount of time) trade Speaker and Listener roles.
The goal of this exercise is to share something about your own recovery or wellness that you think is important for your partner to understand.
Use the Speaker Listener Guidelines found in the Menu page to help with sharing and listening.
Sit facing each other, with the Speaker holding the My Recovery – My Wellness card deck. Thumb through the deck until you find several cards that contain something
you want to share to help your partner understand something about your recovery (or wellness) experience. You can modify ideas from the card deck or share something relevant to you that may not be in the deck. You can include what you feel is going well and/or share something about some of the struggles you may be having. This conversation is about you and your recovery, not about the relationship or relationship recovery.
The Listener’s job is to just listen and try to understand. You can ask questions to clarify and to help you understand. Do not express approval or disapproval, or problem-solve, or offer your opinion. This is about listening and taking in what your partner is saying.
Remember these are the Speaker’s experiences, feelings and needs. Respond simply with an accepting presence and an indication that you hear and understand. You do not have to fix, change, or take responsibility for what you hear.
After 15 minutes (or an agreed upon amount of time) trade Speaker and Listener roles.
Instructions The goal for this exercise is to help you and your partner talk about recovery so that it does not become the new “elephant in the living room.” This intervention provides a tool for you to identify and address the impact of recovery on the relationship.
Using the Couple Recovery card deck, split the deck in half and each of you look through your half of the cards. From there, choose several cards that you would be interested in talking about with your partner. Share with each other the cards you picked, then decide which one card you both agree to talk about. Each partner must agree with the suggested question. If either partner is uncomfortable or prefers another question, go through the cards until you can select one card both of you are willing to talk about.
Use the Speaker Listener Guidelines found on the Menu page to help with sharing and listening.
In this exercise couples learn to create a dialogue to discuss their couple recovery. Questions vary but have a theme related to, “How are we doing? What changes are taking place in our relationship since beginning recovery and what do we need to talk about related to these changes?”
This exercise tends to work best initially if partners stick with the Speaker – Listener structure. While it may be tempting at first to move into problem-solving, try to stay with sharing and listening. Suspend your own position and thoughts when in the listening role. The goal is to help each other to feel safe in expressing feelings and perspectives. Over time, these questions may create more of a dialogue and an exchange of thoughts and feelings leading to action or changes.
Decide how long you would like to spend addressing this issue.
When people talk, listen complete.
Most people never listen.
–Ernest Hemingway.
Use the following guidelines that define the Speaker and Listener roles for the Build Recovery Map card deck exercises. It is important to try to stay in these roles until the Speaker feels understood, and then switch roles with the Listener becoming the Speaker.
Share only what you are comfortable sharing. See if you can identify at least one or more feelings you have about what you are sharing. The key is to focus on yourself, not your partner, describe your thoughts, feelings, and needs.
In disclosure, there are different levels of sharing of details and specifics. It is appropriate to limit disclosure to what feels comfortable.
For example, if you share about something you are struggling with, try to identify what is happening for you and how you feel about it. For example, “I am nervous about tomorrow’s office party and how I might exit if I feel uncomfortable about the drinking part.” If you are not comfortable talking about the specific content, you could say “I am thinking through how to handle a situation differently.”
If you share something positive about what is happening in your recovery, you could identity what positive thing happened and how you felt about it. For example, “I had a good meeting tonight. Several people spoke about struggles with perfectionism, and I see how I too really raise the bar for myself and put pressure on myself to not accept my imperfections. It helped to focus on the idea of progress, not perfection.” Sharing less, for example, could sound something like this: “I had a good meeting this evening, several things people said really hit home.”
Finally, while there are different levels of sharing, there are also different reasons. You may simply want to update your partner on what is happening, or you may have a need or a request for your partner.
For example:
The Listener should decide if the request is neutral, helpful, or harmful to his/her own recovery–well- ness.
Take this opportunity to deepen empathy and just listen to what your partner is saying.
Try not to interrupt or add your own thoughts and feelings. The goal is to empathize and validate your partner’s thoughts, feelings and needs. This is the gold standard in communication!
You communicate to your partner that you understand what your partner is expressing and feeling, and that you care.
Empathy has several steps:
You communicate that you understand and accept without judgment your partner’s feelings and that it makes sense to you given your partner’s perspective. The bottom line: Convey, “You have a right to have these feelings.”
Validation has several steps:
Neither empathy nor validation has to do with placating, agreeing, liking, disliking, or determining if something is “true” (from your perspective). Every feeling is valid, based on the person’s perceptions, beliefs and history. Continued dialogue may change that perception or belief, but in healthy relationships partners need to be able to express their true thoughts and feelings at the time.
An example of an empathic and validating response would be to say something like this:
1. So you are feeling… (upset, happy, fearful, confused, excited, etc.)
2. About… (name the specific events, people, circumstances related to feeling),
3. Because… (express the reason, motivation, belief, you hear that explains the speaker’s feelings)
4. And I can understand why you feel this way; or “That makes sense.”
1, 2, 3 above reflects empathy. 4 supports validation
OUTLINE
The Philosophy of the Therapy
CONFLICT MANAGEMENT
QUESTION AND ANSWER SESSION
BUILDING FRIENDSHIP AND SHARED MEANING
PROCESS OF THE THERAPY
SUMMARY
WHAT’S NEXT: ADDITIONAL TRAINING QUESTION AND ANSWER SESSION
Copyright © 2000–2016 by Dr. John M. Gottman and Dr. Julie Schwartz Gottman. Distributed under license by The Gottman Institute, Inc.
OUTLINE
THE RESEARCH:
What Makes Relationships Succeed or Fail?
HOW TO ASSESS A RELATIONSHIP:
Using The Sound Relationship House Theory to assess a relationship’s strengths and areas that need improvement.
THE ASSESSMENT SESSIONS:
FILM:
Assessment
QUESTION AND ANSWER SESSION
Copyright © 2000–2016 by Dr. John M. Gottman and Dr. Julie Schwartz Gottman. Distributed under license by The Gottman Institute, Inc.
This is just to see my availability. It is NOT my booking calendar. If days are grey, the schedule is full. If you do see an opening (white), you will need to register for the site and log in to schedule. You must schedule at least 24 hours in advance. Be aware that follow up appointments are also based on availability you see here. To book an appointment you must first register for the site and complete the intake process.
Loading . . .
Text and email are non-secure methods for transmission of personal health care information. It is highly recommended that you use personal email and SMS/MMS addresses only. Do not use addresses associated with work accounts. Individuals who have access to your email and SMS/MMS accounts will also have access to the following information about your care with your therapist
If you agree to email and SMS notices and reminders now, Message and data rates may apply, depending on your mobile phone service plan. You may stop text notification at any time by texting ‘OPTOUT’. To re-subscribe text ‘START’.
You may refuse email and SMS notices and reminders now. However if you refuse notifications, you will need to regularly check the message board for any general notices from your therapist. If reminders and notifications are refused, you can still see upcoming appointments, and book, cancel, and reschedule appointments through the website.
For a full explanation of the TuckerWorks privacy practices see this link: Notice of Privacy Practices
ASL Mailing List
Feeling connected requires seeing all emotions as chances to build a bond. By staying mindful and responding positively to a partner’s bids for connection, you increase the likelihood of another bid to 75%. This creates a positive spiral that strengthens the relationship over time. Ignoring or rejecting these bids, however, triggers a negative spiral, dropping the chance of another bid to less than 25%. Many long-term couples feel stuck in this negative cycle. Gottman Relationship Therapy focuses on recognizing small bids for connection and increasing both their frequency and the times partners turn toward them. This approach stops the negative spiral of distance and builds a positive spiral of connection.
The Sound Relationship House theory explains that trust acts as one of the weight-bearing walls in a relationship. When this wall suffers damage, the entire relationship becomes vulnerable. Responding to our partner’s emotions plays a crucial role in building and rebuilding trust. In Gottman Relationship Therapy, we apply the principles of attunement, even when our partner voices complaints about us. Trust grows when we listen to these complaints without being defensive and allow our partner to influence us. We show this by taking responsibility for hurtful events and making meaningful amends, which helps soothe every wound. Trust also deepens through openness in the relationship. Each partner needs an attitude of “let me help you understand what’s happening in my life.” Trust is further strengthened when we make the relationship a priority. This means honoring promises to our partner, even small ones, above those to friends, family, or work commitments. Fierce loyalty to our partner ensures the foundation of trust remains solid, allowing couples to restore and strengthen their bond.
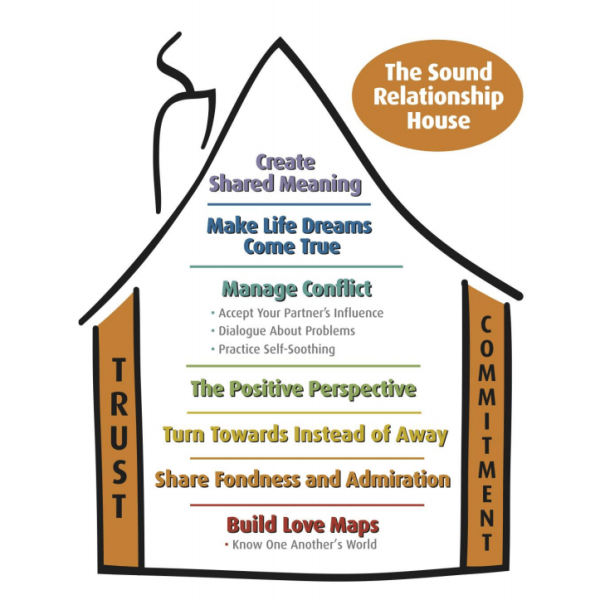
There are four levels to The Sound Relationship House:
Level 1–Friendship. Friendship includes three parts:
Level II—The Positive Perspective. A positive perspective develops when couples maintain a strong friendship. In other words, they keep their Love Maps accurate and up to date, they consistently express fondness and admiration, and turn toward each other’s bids for attention. When this happens, positive feelings naturally outweigh the negative ones. This process strengthens their relationship, fosters a deeper connection, and is the road to intimacy and great sex.
Level III–Regulation of Conflict. This measures how well the couple respectfully communicates and accepts influence from each other during disagreements. It requires a willingness to forgive and to accept the totality of our partners. It also requires each person to allow their partner time to calm down when emotions get in the way of listening. When this works effectively, repair attempts succeed, and both partners find it easier to reach a compromise.
Level IV—Make Life’s Dreams Come True/Create Shared Meaning. These two levels often overlap, as the couple works to honor each other’s dreams while also building a shared sense of meaning. This connection strengthens their bond.
The Walls of the House: The walls of the house consist of the trust and commitment that the couple builds over time. When every part fits together, the relationship becomes strong and secure.
Emotions are seen as a way of getting closer. Increased intimacy is built by turning toward bids for emotional connection. Emotional moments are times to open up and build trust. There has to be trust and safety in the relationship for there to be a great sex life, a fun dating life, and to just enjoy time together. In Gottman Relationship Therapy we analyze what has happened to cause trust to erode and we provide a blueprint to rebuild trust. We identify the behaviors that are causing fear of further emotional hurt and provide principles to help heal. When our partners feel safe from emotional harm and feel connected to us emotionally the result is less disturbing conflict and an environment where rebuilding a sexual relationship is possible. We develop new rituals about initiating sex, how to say no, and how to take no. We identify all elements that put the sexual breaks on and find ways to safely take them off. We clarify the elements that enhance sexual desire and make plans to do more of them. Rebuild sex, romance, and passion in your relationship.
In the Sound Relationship House theory of relationships trust is one of the weight bearing walls. When this wall is damaged the entire relationship is at risk. How we respond to the emotions of our partner is an important component of building and rebuilding trust with your partner. In Gottman Relationship Therapy we practice the principles of attunement even when our partners are complaining about us. Trust is built as we hear complaints non-defensively and take influence from our partners. We demonstrate taking influence by atoning for unfortunate events in meaningful ways. Every wound is soothed. Trust is also built through attitudes of openness in a relationship. Each partner needs to have an attitude of “let me help you know what is happening in my life.” Trust is built by making the marriage a priority. We honor promises to our partners, even small ones, above those to friends, family, or our boss. We are fiercely loyal to our partners. Restore and strengthen the trust in your relationship.
Emotional safety is built through the process of attuning to the bids for our emotional connection. When our partners reach out to us and we reach back with humble understanding, acceptance, and validation they experience us as harmless. We are a safe harbor in the middle of a storm. Habits of ignoring or dismissing our partner’s feelings results in each being on guard, distant, and not safe. Safety is also communicated when our physical behavior says we are harmless. Intimidation, even when it is not intentional will always destroy feelings of safety. In heterosexual relationships, the men are often physically larger with deeper and louder voices than their female partners. Men often need to be doubly aware of what they are communicating physically. In Gottman Relationship Therapy we use video and physiological monitoring to help increase awareness of ways to increase safety when talking about troubles. Make your relationship a safe harbor.
Emotions are seen as a way of getting closer. Increased intimacy is built by turning toward bids for emotional connection. Emotional moments are times to open up and build trust. There has to be trust and safety in the relationship for there to be a great sex life, a fun dating life, and to just enjoy time together. In Gottman Relationship Therapy we analyze what has happened to cause trust to erode and we provide a blueprint to rebuild trust. We identify the behaviors that are causing fear of further emotional hurt and provide principles to help heal. When our partners feel safe from emotional harm and feel connected to us emotionally the result is less disturbing conflict and an environment where rebuilding a sexual relationship is possible. We develop new rituals about initiating sex, how to say no, and how to take no. We identify all elements that put the sexual breaks on and find ways to safely take them off. We clarify the elements that enhance sexual desire and make plans to do more of them. Rebuild sex, romance, and passion in your relationship.